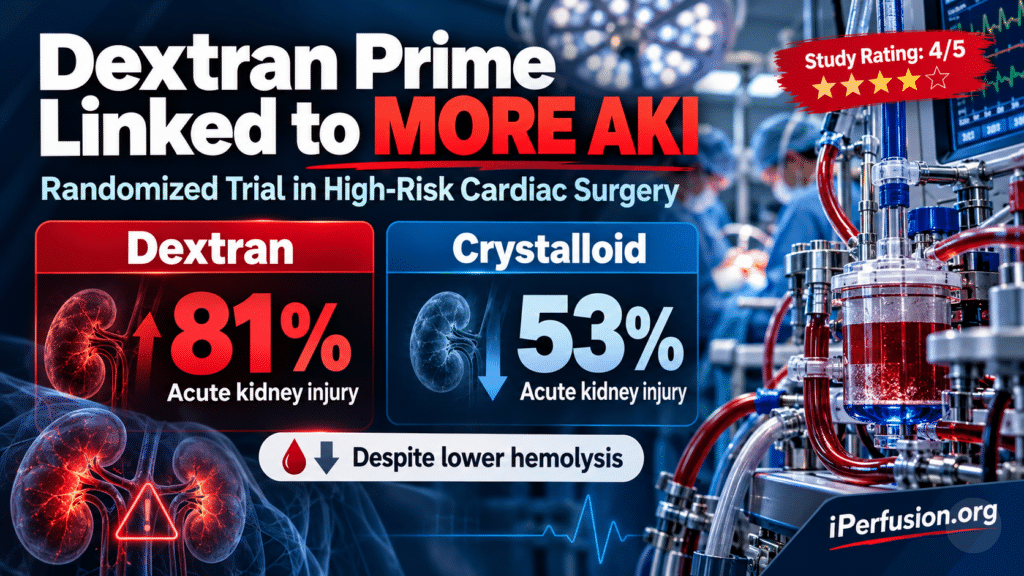
Research summary: In a three-country, double-blinded randomized trial of high-risk adults undergoing cardiac surgery with cardiopulmonary bypass, dextran priming was associated with significantly more postoperative acute kidney injury than crystalloid priming (81% versus 53%). Although dextran reduced measured hemolysis and intraoperative net fluid balance, these surrogate improvements did not translate into renal protection. The study ended early, with 92 analyzed patients versus 366 planned.
Why this priming study matters
Priming strategy during cardiopulmonary bypass (CPB) can influence hemodilution, colloid oncotic pressure, hemolysis and fluid balance. Those physiological measures, however, do not necessarily predict kidney outcomes. Juvakka and colleagues tested whether dextran-based priming could reduce postoperative acute kidney injury (AKI) among patients already considered at particularly high risk. Rather than confirming earlier encouraging pilot observations, this randomized trial found substantially more AKI in patients given dextran. That clinically important signal deserves careful attention alongside the study’s early termination and limited sample size.
Multicenter randomized design
This prospective, double-blinded randomized controlled trial enrolled adults undergoing elective or urgent cardiac surgery with CPB at three centers in Sweden, Denmark and Germany. Eligibility required a predicted postoperative AKI risk of at least 50%, assessed using an AKI risk score; emergency surgery, preoperative dialysis, sepsis/endocarditis and contraindications to dextran were among the exclusions. Randomization was stratified by reduced estimated glomerular filtration rate and anticipated CPB duration. A separate perfusionist prepared the assigned prime, while the operating perfusionist, other clinical teams and patients remained blinded. The investigators planned to enroll 366 patients, but recruitment stopped after 101 had entered screening/enrollment; the principal analysis included 92 patients, 43 assigned to dextran and 49 to standard care.
Priming solutions and perfusion protocol
The intervention was PrimECC (XVIVO Perfusion), a physiological salt solution containing dextran 1 and dextran 40. The comparison prime comprised Ringer’s acetate and mannitol. Prime volumes followed local practice, generally 1,000–1,500 mL, and retrograde autologous priming was prohibited. Nonpulsatile bypass was performed at a flow of 2.4–2.6 L/min/m², targeting mixed venous oxygen saturation above 70%. Red-cell transfusion or hemofiltration was permitted under the specified low-hematocrit and low-venous-saturation conditions. These details are crucial: the findings concern the complete dextran-versus-Ringer’s-acetate/mannitol protocols in high-risk adults, not every colloid formulation or every CPB circuit.
Primary endpoint: more AKI with dextran
The primary endpoint was KDIGO-defined AKI within 96 hours after surgery based on serum creatinine. AKI developed in 35 of 43 patients (81%) receiving dextran compared with 26 of 49 (53%) receiving crystalloid: risk ratio 1.53, 95% confidence interval 1.15–2.06, p = 0.004. That is a 28-percentage-point absolute difference in this enrolled population, contrary to the investigators’ renal-protection hypothesis. Serum creatinine was higher in the dextran group at postoperative measurements through 72 hours, and corresponding estimated glomerular filtration was lower. At 48 hours, mean estimated glomerular filtration was 43 versus 53 mL/min/1.73 m² (p = 0.03). The paper’s 48-hour AKI-stage figure shows a shift toward more grade 1–2 AKI, rather than a clear difference in grade 3 events.
Hemolysis and fluid balance: favorable surrogate signals
Not all physiological endpoints moved in the same direction as kidney injury. During CPB, plasma-free hemoglobin at 60 minutes averaged 0.18 ± 0.09 g/L in the dextran group versus 0.34 ± 0.23 g/L with standard care (p < 0.001), suggesting less measured hemolysis. Median intraoperative net fluid balance was 1,270 mL with dextran versus 1,850 mL in controls (p = 0.006). The authors also reported greater hemofiltration in the dextran group. Despite these seemingly favorable fluid and hemolysis measures, AKI occurred more frequently. The study therefore cautions against assuming that improved surrogates, on their own, demonstrate renal protection.
Dialysis, adverse events and safety
Postoperative renal replacement therapy within 96 hours was required in 3 of 43 dextran patients (7%) and 2 of 49 controls (4%), a nonsignificant difference (p = 0.66). The small sample provides little precision for uncommon outcomes such as dialysis or death. Serious adverse events occurred in 10 of 42 dextran recipients and 14 of 50 controls in the as-treated safety population. Three deaths were described across the groups; investigators judged none related to the intervention. No anaphylactic reactions were reported. These observations should not be interpreted as definitive evidence of equivalence for serious complications.
Potential explanations and confounding
The discussion considers possible renal effects of dextran, including tubular precipitation and changes in glomerular filtration associated with high oncotic pressure. These remain hypotheses rather than mechanisms established by this trial. Group differences also deserve attention: coronary bypass procedures and urgent cases were numerically more common in the dextran arm, and its median CPB duration was longer (1.8 versus 1.4 hours). Although baseline risk scores and measured renal function were broadly comparable, a trial this small may leave clinically relevant imbalances after randomization. The crystalloid comparator also included mannitol, so this experiment should not be construed as a comparison with every contemporary balanced-crystalloid-only prime.
Strengths and limitations
The multicenter design, prospective randomized allocation, deliberate blinding and predefined kidney endpoint strengthen the evidence. Nonetheless, the study achieved only 92 analyzed participants against 366 planned, after pandemic interruptions and slow recruitment. Only about one in 15 screened candidates met the demanding high-risk eligibility criterion. AKI classification relied on serum creatinine rather than urine-output criteria, and follow-up for the primary endpoint ended at 96 hours. The authors did not complete planned cerebral and urine tubular-injury biomarker analyses. Early termination and treatment-group procedural differences restrict confidence in effect-size precision and generalizability; they do not erase the statistically significant observed AKI signal.
Implications for perfusion practice
For perfusion teams, this study challenges the assumption that a higher-oncotic-pressure prime or reduced plasma-free hemoglobin automatically improves renal outcomes. In the studied high-risk adult population, dextran-based priming was associated with more AKI despite lower hemolysis and a less-positive fluid balance. These findings do not support adopting the tested dextran prime specifically to prevent AKI in similar patients. They also do not establish that every dextran-containing or colloid priming formulation is harmful in every patient group. Protocol decisions should incorporate patient risk, current evidence, institutional standards and multidisciplinary review; confirmatory larger trials would help clarify the mechanism and clinical generalizability.
Keywords: Dextran, Crystalloid Priming, Acute Kidney Injury, Cardiopulmonary Bypass, Hemolysis, Renal Protection, Perfusion, Randomized Controlled Trial, PrimECC, Cardiac Surgery.
Source: Juvakka O, Wallinder A, Møller-Sørensen PH, Matschke K, Jeppsson A, Lannemyr L. Dextran vs. Crystalloid Priming Solution in Cardiac Surgery: A Randomized Trial on Acute Kidney Injury. Acta Anaesthesiologica Scandinavica. 2025;70:e70139. doi:10.1111/aas.70139. Open access under CC BY 4.0. Funding was provided by XVIVO Perfusion; an author was employed by XVIVO and another reported consultancy with the company. This independent IPA educational appraisal is not the original study.