Early left ventricular (LV) dysfunction after VSD repair can occur even when preoperative ejection fraction is normal. A retrospective study of 409 children found that roughly one in five developed an ejection fraction below 55% during the postoperative admission. Preoperative myocardial strain and myocardial work measurements identified differences that conventional ejection fraction did not capture. Although ejection fraction subsequently recovered, the early dysfunction group showed less favorable symptoms and myocardial mechanics during follow-up.
Study Population and Measurements
Zhao and colleagues reviewed isolated surgical ventricular septal defect (VSD) repairs performed at Yunnan Fuwai Cardiovascular Hospital between September 2020 and December 2023. Children were aged 0–14 years, with a median age of 3 years, and all had a preoperative LV ejection fraction of at least 55%.
The analysis excluded important higher-risk groups, including children with additional congenital defects other than a patent foramen ovale and those with major perioperative complications such as low cardiac output syndrome, pulmonary hypertensive crisis, tamponade, or a residual shunt greater than 3 mm. Its results therefore describe a selected surgical cohort.
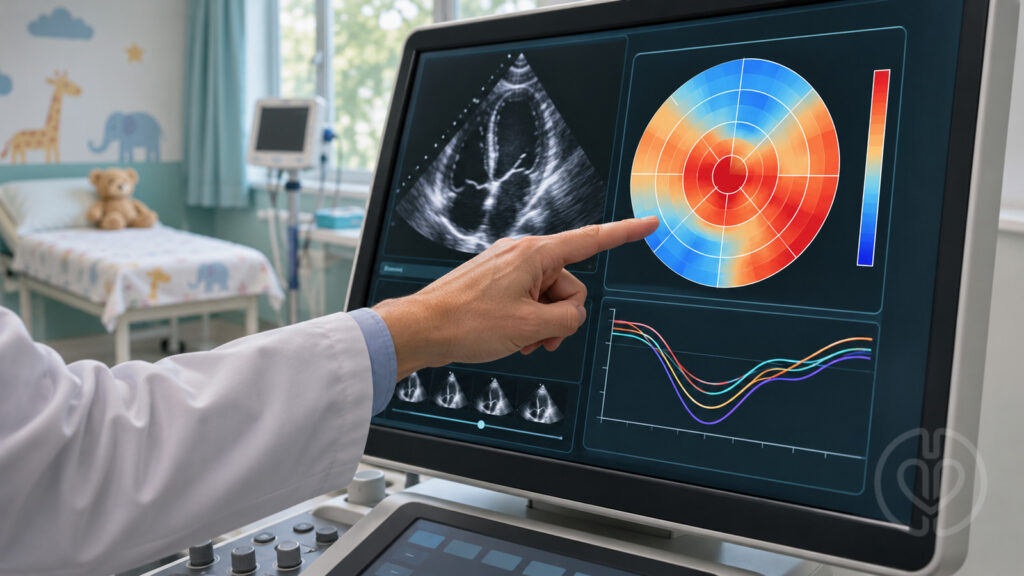
Investigators combined conventional echocardiography with global longitudinal strain (GLS) and noninvasive myocardial work measurements. GLS measures deformation of the myocardium; the study expressed it as an absolute value. Myocardial work indices combine deformation with an estimated LV pressure curve derived from blood pressure. Global work index (GWI) estimates total work, while global work efficiency (GWE) describes the proportion of constructive work relative to constructive plus wasted work.
Early LV Dysfunction After VSD Repair
Postoperative LV dysfunction occurred in 82 of 409 children (20.05%). Thirty had an ejection fraction of 50% to below 55%, 32 had values of 40% to below 50%, and 20 had values below 40%. Before surgery, mean ejection fraction was similar in those who later developed dysfunction and those who did not.
In contrast, the dysfunction group had lower preoperative GLS, GWI, and GWE, along with greater LV dilation. Multivariable analyses associated lower strain or work measurements, larger indexed LV end-diastolic volume, moderate-to-severe estimated pulmonary arterial systolic pressure, large VSD size, and longer cardiopulmonary bypass (CPB) duration with early postoperative dysfunction. Correlated imaging measures were assessed in separate models.
Prediction Beyond Ejection Fraction
Models combining myocardial work indices with clinical or conventional echocardiographic measures achieved areas under the receiver operating characteristic curve of 0.848–0.883. Reported sensitivities ranged from 81.7% to 86.8%, with specificities of 74.6%–84.4%.
These results suggest that strain and myocardial work may add information when ejection fraction appears preserved. However, the models were evaluated within this single-center dataset and lacked external validation. Their performance does not establish a ready-to-use clinical risk calculator or universal treatment threshold.
Bypass Time and Perioperative Recovery
Median CPB duration was 94 minutes in the dysfunction group versus 70 minutes in the preserved-function group. Median aortic cross-clamp time was 63 versus 37 minutes. Children with dysfunction also had longer median ventilation duration (14 versus 8 hours), ICU stay (3 versus 1 day), and hospital stay (19 versus 14 days). Milrinone use was more frequent.
For perfusion teams, these associations support considering the child’s preoperative myocardial reserve and the complexity of repair alongside the bypass course. They do not show that bypass duration alone caused dysfunction or that shortening CPB by a particular amount would prevent it. Larger defects and more extensive repair can contribute to both longer bypass exposure and a more difficult recovery. The study did not compare cardioplegia formulations, perfusion targets, or myocardial protection strategies.
Recovery of Ejection Fraction and Symptoms
The authors reported normalization of ejection fraction in 68 of the 82 affected children by one month, 80 by three months, and all 82 by six months. Nevertheless, GLS, GWI, and global constructive work remained less favorable in the early dysfunction group during follow-up, and Ross functional classification improved less favorably over 12 months. Normalization of ejection fraction therefore did not eliminate every measured difference between groups.
These recovery findings require caution: attendance for follow-up examinations fell from 91.7% at one month to 62.8% at 12 months. The reported recovery proportions should be interpreted alongside that incomplete surveillance. Persistent differences in strain or symptoms also do not, by themselves, prove irreversible myocardial injury.
Limitations and Clinical Interpretation
The retrospective design cannot establish causation. Selection exclusions, incomplete follow-up, residual confounding, and the cohort’s relatively older age at repair limit generalization, particularly to infants undergoing earlier surgery or patients with major postoperative complications. Ross classification includes subjective symptom assessment, and cuff-based blood pressure may imperfectly represent LV systolic pressure when calculating myocardial work.
An early fall in ejection fraction after shunt closure may partly reflect abrupt changes in preload and ventricular geometry rather than intrinsic injury alone. The practical message is that preserved preoperative ejection fraction may not capture the entire risk profile. Strain and myocardial work are promising complementary assessments, but prospective validation is needed before using these findings to change clinical protocols.
Original Article
Zhao W, Li W, Wang T, et al. Predictors and outcomes of early left ventricular dysfunction in paediatric patients postoperative for ventricular septal defect: a retrospective cohort study based on myocardial strain and work. BMC Pediatrics. 2026;26:1084. doi:10.1186/s12887-026-07470-6.
The authors declared no competing interests. Funding was reported from Chinese national and Yunnan research programs and institutional projects. The unchanged source article is available below under its stated CC BY-NC-ND 4.0 license.