External wrapping of the ascending aorta was associated with shorter cardiopulmonary bypass and cross-clamp times than ascending aorta replacement in a new systematic review of 851 patients. However, the absence of statistically significant mortality differences does not establish equivalent safety or durability. The authors retain replacement as the gold standard when aortic intervention is indicated and describe wrapping as a possible option for carefully selected patients.
What Was Studied?
Dell’Aquila and colleagues reviewed eight retrospective comparative studies involving 433 patients treated with external wrapping and 418 treated with replacement. PubMed, Embase, and Web of Science were searched through October 2025. The review was registered in PROSPERO and followed PRISMA reporting guidance.
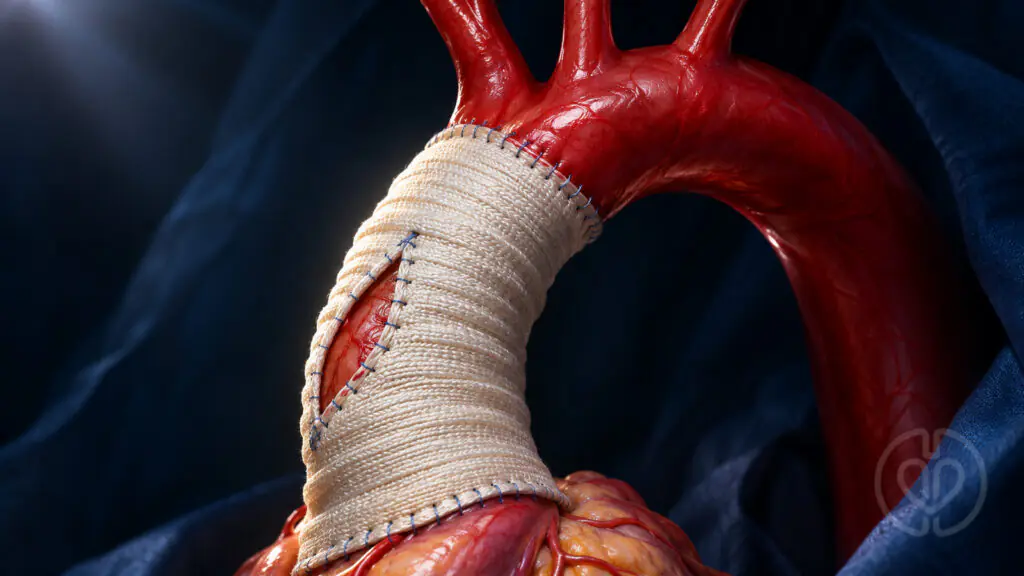
External wrapping places a prosthetic support around the native ascending aorta. Replacement removes the diseased segment and substitutes a vascular graft. Some wrapping cohorts also underwent reduction aortoplasty, in which the native aorta is surgically reduced before external reinforcement. Pooling these approaches adds technical variability to the comparison.
The mean follow-up was 3.9 years. Many patients underwent concomitant aortic valve surgery, and the cohorts represent selected surgical populations rather than all patients with ascending aortic dilation.
External Wrapping of the Ascending Aorta: Key Findings
| Outcome | Reported comparison | Interpretation |
|---|---|---|
| 30-day/in-hospital mortality | OR 0.60; 95% CI 0.27–1.30 | No statistically significant difference |
| Midterm mortality | IRR 0.97; 95% CI 0.57–1.66 | No statistically significant difference |
| Cardiopulmonary bypass time | 42.4 minutes shorter with wrapping | Reported unweighted mean absolute difference |
| Aortic cross-clamp time | 30.6 minutes shorter with wrapping | Reported unweighted mean absolute difference |
| ICU stay | 22.6 hours shorter with wrapping | Reported unweighted mean absolute difference |
| Hospital stay | 2.4 days shorter with wrapping | Reported unweighted mean absolute difference |
Stroke, acute kidney injury, wound infection, and reoperation for bleeding did not differ significantly. These findings remain imprecise: for example, the stroke odds ratio was 0.67 with a 95% confidence interval of 0.23–1.93, and the acute kidney injury odds ratio was 0.66 with a confidence interval of 0.22–1.96. The intervals permit clinically relevant differences in either direction.
Why the Time Savings Need Context
Seven studies with 616 patients contributed to the operative-time analyses. Pooled standardized mean differences favored wrapping for bypass time (−2.46; 95% CI −3.49 to −1.43) and cross-clamp time (−2.12; 95% CI −3.18 to −1.07). Between-study heterogeneity was very high: I² was 96.0% and 96.4%, respectively.
The direction consistently favored wrapping, but the magnitude varied markedly across studies. Differences in surgical complexity, concomitant procedures, anatomy, and patient selection may explain part of the association. The reported 42.4-minute bypass difference should not be interpreted as a causal treatment effect or used as a fixed planning allowance.
The Groups Were Different Before Surgery
Patients undergoing wrapping were older on average, 61.8 versus 59.2 years, but had smaller baseline ascending aortic diameters, 48.6 versus 52.7 mm. Bicuspid aortic valve disease was reported in 51.6% versus 65.0% of patients with available data.
These differences matter because the decision to wrap or replace was not randomized. Frailty, operative risk scores, detailed anatomy, urgency, and surgeon selection criteria were inconsistently reported. Aggregate data cannot fully adjust for these factors. A meta-analysis of observational studies does not remove the selection bias within those studies.
Relevance for Perfusion Practice
For perfusion teams, the report places operative exposure at the center of the discussion. A less extensive aortic procedure may accompany shorter bypass and myocardial ischemic times, but the study did not test a perfusion protocol or prove that time reduction improved organ outcomes.
During the team briefing, the practical questions remain the planned aortic and valve procedures, expected cannulation and clamp strategy, myocardial protection, and the contingency plan if the intended operation changes. These are practice considerations prompted by the comparison, rather than interventions evaluated by the review. The findings do not support reducing perfusion readiness or changing anticoagulation, temperature, or cardioplegia protocols solely because wrapping is planned.
Durability and Surveillance Remain Unresolved
Follow-up proximal and midascending aortic diameters did not differ significantly, but imaging methods, measurement locations, and surveillance schedules varied. Aortic-related mortality and reintervention were not reported consistently enough for dependable comparative conclusions.
The authors discuss potential wrapping complications, including migration, erosion or injury of the native wall, recurrent dilation, and enlargement of adjacent unwrapped segments. These are concerns from the wider literature, not complications shown to be more frequent in this pooled comparison. Limited follow-up and uncommon late events leave substantial uncertainty about long-term durability.
Limitations and Clinical Interpretation
All eight included studies were retrospective. Techniques, materials, selection criteria, and associated operations differed, while the sample was too small to resolve uncommon adverse events reliably. Wrapping alone and wrapping with reduction aortoplasty were combined. The analysis therefore supports further study and selective multidisciplinary discussion, rather than a general change in surgical strategy.
The paper also reports different early-mortality estimates in its abstract and main analysis: the abstract gives OR 0.61 (95% CI 0.24–1.56), while the Results and Table IV give OR 0.60 (95% CI 0.27–1.30). Both are nonsignificant; this summary uses the main-analysis estimate. Neither demonstrates equivalence or noninferiority.
The authors report no study funding and no conflicts of interest related to the study. Ascending aorta replacement remains their reference surgical approach; external wrapping may have a selective role when anatomy and overall operative risk make it appropriate, but its comparative durability remains unproven.
Original Article
Dell’Aquila M, Sherman N, O’Connor K, et al. External wrapping of the ascending aorta versus ascending aorta replacement: Systematic review and meta-analysis. Surgery. 2026;199:110538. doi:10.1016/j.surg.2026.110538.
The source PDF is unchanged. The cover is an AI-generated editorial illustration, not a technical surgical guide.